Updated ACR Guidelines for Osteoarthritis Treatment
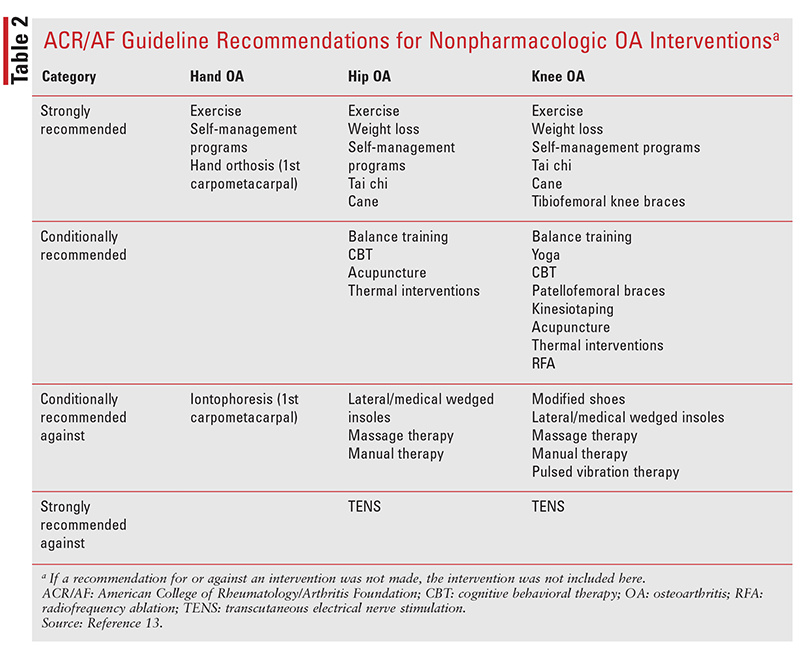
Recent updates to osteoarthritis clinical guidelines from the American College of Rheumatology highlight a shifting medical consensus regarding which management strategies effectively modify disease progression and which interventions fail to alter joint pathogenesis. As clinical practices evolve to prioritize evidence-based non-pharmacological care and targeted therapies over ineffective modalities, patients face critical decisions regarding their long-term treatment plans.
Key Clinical Takeaways:
- The American College of Rheumatology has updated its clinical guidance to emphasize high-value interventions while discouraging unproven therapies for knee, hip, and hand osteoarthritis.
- Clinical trials and systematic reviews demonstrate that structured exercise and targeted weight management remain foundational, whereas certain complementary supplements lack robust double-blind placebo-controlled data.
- Patients experiencing persistent joint morbidity should consult vetted specialists through dedicated directories such as [Relevant Clinic/Professional/Service] to establish personalized, guideline-adherent care protocols.
Evolving Standards of Care in Osteoarthritis Management
Osteoarthritis remains a leading cause of musculoskeletal disability worldwide, characterized by the progressive degradation of articular cartilage, subchondral bone remodeling, and chronic synovial inflammation. According to updated recommendations issued by the American College of Rheumatology, the standard of care increasingly emphasizes conservative, patient-specific measures designed to preserve joint architecture and mitigate pain without exposing patients to unnecessary adverse events. Medical directors and rheumatology research groups stress that identifying appropriate interventions early in the disease course can significantly alter functional outcomes.
For individuals navigating complex treatment adjustments or seeking specialized diagnostic imaging, connecting with verified clinical networks is essential. Reviewing provider credentials through portals like [Relevant Clinic/Professional/Service] ensures that patients receive care aligned with current peer-reviewed benchmarks.
Evaluating What Works: Efficacy of Core Interventions
Clinical data consistently support a core set of non-pharmacological and pharmacological modalities that demonstrate statistically significant improvements in pain scores and functional capacity. Supervised land-based exercise programs, customized physical therapy regimens, and structured weight loss protocols top the hierarchy of clinical recommendations. These interventions reduce mechanical load across vulnerable articular surfaces, lowering systemic inflammatory markers associated with joint destruction.
Pharmacologically, topical nonsteroidal anti-inflammatory drugs (NSAIDs) remain a primary recommendation for localized osteoarthritis, offering localized analgesia with a reduced systemic toxicity profile compared to oral alternatives. Conversely, the clinical utility of intra-articular hyaluronic acid injections and certain arthroscopic procedures continues to face scrutiny in light of recent meta-analyses showing limited long-term disease modification.
When systemic pharmacological management or physical rehabilitation fails to control advancing symptoms, timely referral to an orthopedic specialist is warranted. Patients can evaluate local surgical and non-surgical options by consulting [Relevant Clinic/Professional/Service] for vetted musculoskeletal care providers.
Addressing Ineffective Modalities and Clinical Pitfalls
Despite widespread patient usage, several popular interventions lack the rigorous randomized controlled trial backing required to justify routine clinical employment. Dietary supplements, including specific over-the-counter nutraceutical combinations, frequently fail to demonstrate reproducible efficacy in large-scale, double-blind trials. Relying on unverified modalities can delay the implementation of evidence-based therapies, potentially worsening joint morbidity.
Healthcare providers must navigate these clinical discrepancies carefully, educating patients on the risks of contraindications and the financial burden of unproven treatments. Establishing a clear dialogue between patients, primary care physicians, and specialists helps eliminate ineffective regimens from ongoing care plans.
As clinical guidelines continue to adapt to emerging data, maintaining continuity with accredited health professionals remains the most reliable strategy for managing chronic joint disease. To explore comprehensive diagnostic evaluations and evidence-based treatment plans, consult vetted specialists via [Relevant Clinic/Professional/Service].
Disclaimer: The information provided in this article is for educational and scientific communication purposes only and does not constitute medical advice. Always consult with a qualified healthcare provider regarding any medical condition, diagnosis, or treatment plan.